
A high protein diet for weight loss helps in three measured ways: protein is more filling, costs more energy to digest, and protects muscle while you eat less. In trials lasting weeks to months the advantage was real but modest. In trials lasting a year or more it mostly disappeared, and what decided the outcome was whether people kept going.
Listen to this article, about 10 minutes. A synthetic voice reads the article and announces each section title as it begins; tables are read row by row and the questions at the end are left out.
Recorded 1 October 2026 from the article as published that day. Press a chapter to jump there; the highlighted line is what is playing. A play button sits beside every section heading, and once you scroll past this player a bar at the bottom of the screen keeps the controls in reach. Tap or click any sentence to hear the reading start from there.
On this page: the protein intakes seven studies actually used, set out in one cited table, and what the trials lasting a year or more found once the novelty wore off.
Think you already know this? Five questions, one minute.
Every answer is on this page. Answer from what you know now; the page fills in the rest.
-
1. In the 2024 review of diet induced thermogenesis, roughly what share of protein calories goes on processing it?
Protein costs about 20 to 30 percent of its calories to process, against 5 to 10 for carbohydrate and 0 to 3 for fat, per the 2024 narrative review. Read the section
-
2. What is the adult protein allowance set by the US Food and Nutrition Board?
The allowance is 0.8 g per kg a day, the amount that prevents progressive lean tissue loss in most adults, as set out in this review of the US recommendations. Read the section
-
3. How did Wycherley and colleagues describe the benefits of higher protein in their pooled short trials?
The Wycherley 2012 meta analysis of 24 trials called the benefits for weight, fat mass and lean mass modest. Read the section
-
4. In the three year PREVIEW trial, what did the higher protein, lower glycaemic index diet change?
PREVIEW found hunger fell further on the higher protein diet from 52 weeks on, with no difference in weight regain between groups. Read the section
-
5. What did the 2018 Devries meta analysis find about kidney function in people without kidney disease?
Across 28 papers, Devries and colleagues found changes in kidney function did not differ; people with kidney disease are a separate case, per the National Kidney Foundation. Read the section
Protein has had a better decade than any other nutrient. It now appears on cereal boxes, crisps and, somewhere, probably a scented candle. Underneath the marketing there is a solid body of trials, and they say something more useful and less exciting than the packaging does.
What does a high protein diet for weight loss actually change?
Three mechanisms have been measured rather than merely asserted. The first is fullness. In a feeding trial by Weigle and colleagues, raising protein from 15 to 30 percent of energy while carbohydrate stayed the same led people who could eat as much as they liked to eat about 441 fewer calories a day on their own, with no instruction to cut back. Satiety ratings rose too.
The second is the energy cost of digestion. A 2024 review of diet induced thermogenesis puts it at roughly 20 to 30 percent of the calories in protein, against 5 to 10 percent for carbohydrate and 0 to 3 percent for fat. Worked through on a single portion: 30 grams of protein carries about 120 calories, of which roughly 24 to 36 go on processing it. The same 120 calories of carbohydrate costs about 6 to 12. The difference is somewhere around 12 to 30 calories. Real, and about the size of a biscuit.
The third is muscle. When people eat less, some of what they lose is lean tissue. Higher protein reduces that loss, which matters for strength and, in later life, for staying independent. It is also why the lean mass figures in these trials look better than the weight figures. For what muscle does and does not do to resting metabolism, see how many calories muscle actually burns.
How much protein did the weight loss trials actually use?
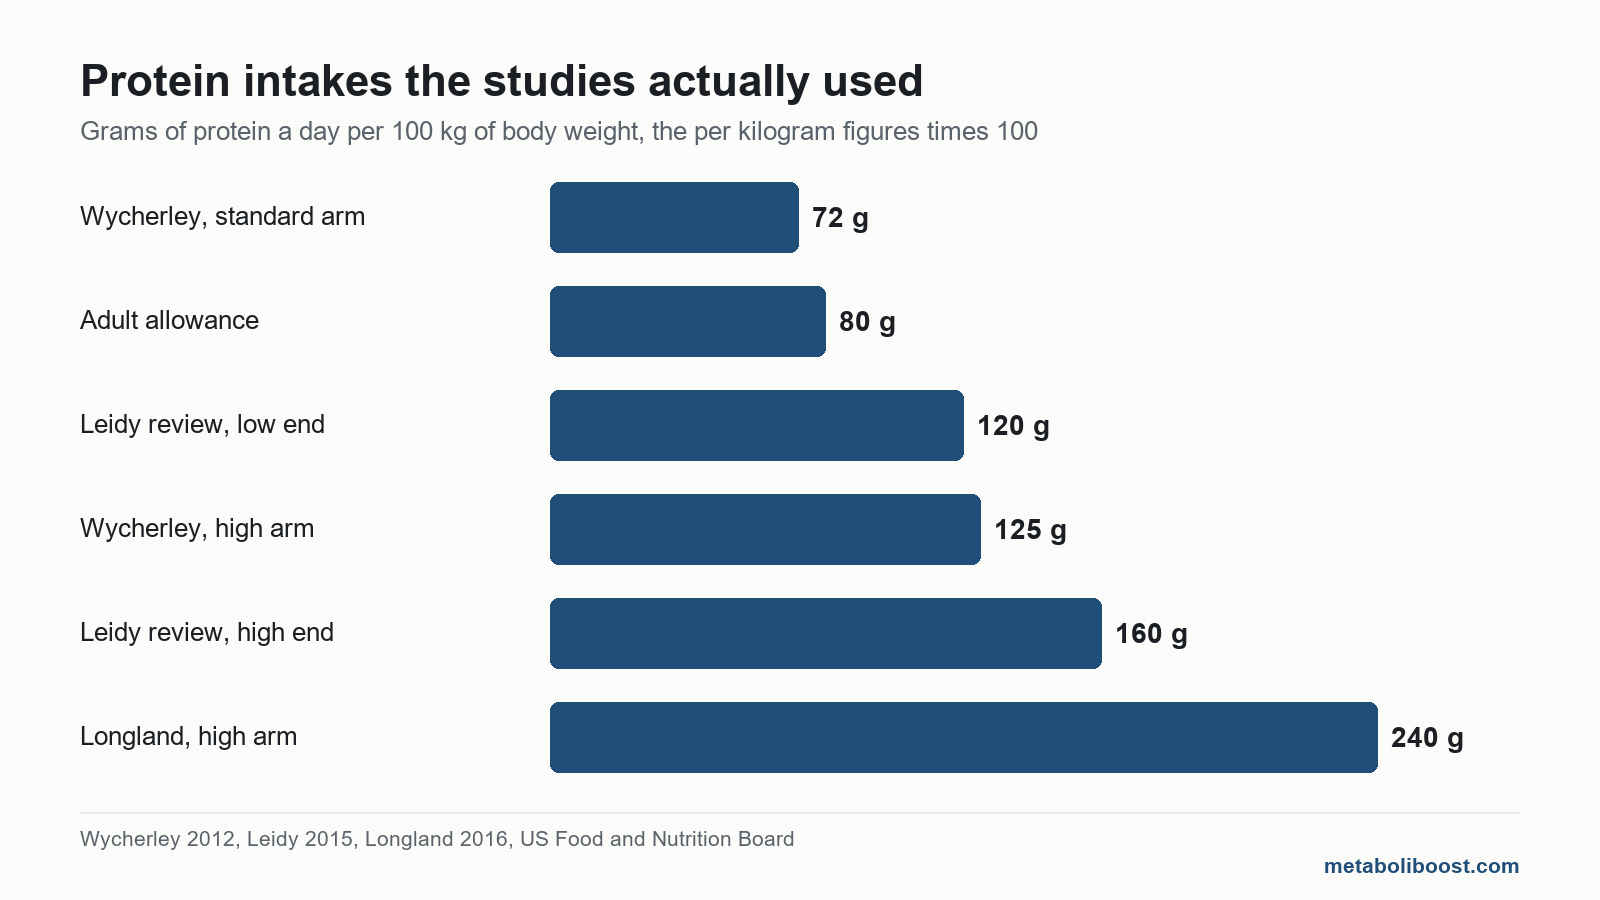
Plan pages tend to give a number without saying where it came from. Here is where the numbers actually came from. The adult allowance is 0.8 grams per kilogram of body weight a day, set by the US Food and Nutrition Board as the amount that prevents progressive loss of lean tissue in most people. The weight loss trials mostly sat between about 1.2 and 1.6.
| Study | Who and how long | Higher protein arm | Comparison arm |
|---|---|---|---|
| Wycherley 2012, meta analysis | 24 randomised trials, adults eating less | About 1.25 g per kg a day | About 0.72 g per kg a day |
| Leidy 2015, review | Summary of weight loss and maintenance trials | 1.2 to 1.6 g per kg a day, about 25 to 30 g a meal | The 0.8 g per kg adult allowance |
| Kim 2016, meta analysis | Older adults losing weight | Above 1.0 g per kg a day | Below 1.0 g per kg a day |
| Longland 2016, trial | 40 young men, hard training six days a week, 4 weeks | 2.4 g per kg a day | 1.2 g per kg a day |
| Weigle 2005, trial | Adults eating as much as they liked | 30 percent of energy | 15 percent of energy |
| DIOGenes 2010, trial | 773 adults keeping lost weight off, 26 weeks | 25 percent of energy | 13 percent of energy |
| PREVIEW 2021, trial | 2,223 adults with prediabetes, 3 years | 25 percent of energy | 15 percent of energy |
Two things in that table are easy to miss. The Longland arm at 2.4 grams was young men training hard six days a week for four weeks, which is not most people reading this. And the trials stated as a percent of energy are not directly comparable with the per kilogram ones, because 25 percent of a small intake and 25 percent of a large one are different amounts of food.

How big was the effect in the short trials?
The largest pooled analysis of short trials, Wycherley and colleagues in 2012, compared 24 randomised trials in which both groups ate the same reduced number of calories and only the protein share differed. The higher protein groups did a little better on weight and fat mass, held on to more lean mass, and lost less resting energy expenditure. The authors called the benefits modest, and that word is doing honest work: across the pooled trials the difference between the arms was small enough that an ordinary week of water fluctuation would hide it on a bathroom scale.
In older adults, a 2016 meta analysis by Kim and colleagues found that those eating more than 1.0 gram per kilogram while losing weight lost more fat and less lean mass than those eating less. In the Longland trial, the higher protein group gained lean mass during a steep deficit while the lower protein group held level. That result is real, and it belongs to people training at an intensity few readers will match. For the broader question of who can lose fat and gain muscle at the same time, the training mattered as much as the protein.
| What protein is said to do | The plan page version | What the trials show | Source |
|---|---|---|---|
| Fullness | Protein is the most filling of the three macronutrients | Supported. Appetite ratings and spontaneous intake fell in feeding trials | Weigle 2005 |
| Calories spent digesting | Protein burns itself off | About 20 to 30 percent of protein calories go on processing it, against 5 to 10 for carbohydrate | 2024 narrative review |
| Muscle kept while eating less | Protects lean mass | Supported in pooled trials and in older adults | Wycherley 2012, Kim 2016 |
| Long term weight | Keeps the weight off for good | No difference at 12 months or more in pooled trials | Schwingshackl 2013 |
| Hunger over years | You will never feel hungry | Hunger fell further over three years, weight regain did not differ | PREVIEW 2021 |
What the trial protein levels come to at your weight
This multiplies your weight by the intakes the studies above used and shows the arithmetic. It is not a target, not a plan and not a prediction of any change in weight. Anyone with kidney disease should ask their doctor before eating more protein.
Multipliers from the US adult allowance (0.8 g per kg) and the 1.2 to 1.6 g per kg range in the Leidy 2015 review. Grams of protein in food, not grams of food.
Does the advantage last beyond the first year?
This is the part the plan pages leave out. When Schwingshackl and Hoffmann pooled trials of low fat diets lasting 12 months or more, comparing more than 25 percent of energy from protein with less than 20, they found no difference in weight, fat mass or waist circumference. The one measure that differed was fasting insulin, which fell further on higher protein. The authors wrote that a blanket recommendation for high protein diets was not supported.
The European DIOGenes trial looked at keeping weight off rather than losing it. Of 938 adults who started a low calorie phase, 773 went on to one of five maintenance diets for 26 weeks. The most telling number is not about weight at all: 26.4 percent dropped out of the higher protein groups against 37.4 percent of the group eating less protein with higher glycaemic index carbohydrate. People stayed with the diet that left them less hungry, and staying is what the result depended on.
Then PREVIEW, the longest and largest of them, followed 2,223 adults with prediabetes for three years after an eight week weight loss phase. From the first year onwards, hunger fell further on the higher protein, lower glycaemic index diet. Weight regain did not differ between the groups. Protein made the effort feel easier; it did not, on its own, make the result different. For the long game in general, see why keeping weight off is the hard part.

Who should talk to a doctor before eating more protein?
For people with healthy kidneys, a 2018 meta analysis by Devries and colleagues of 28 papers and more than 1,300 participants found that changes in kidney function did not differ between higher and lower or normal protein diets, including in people with obesity, high blood pressure or type 2 diabetes.
Chronic kidney disease is different. The National Kidney Foundation advises that people with kidney disease often need to limit protein, and the amount depends on the stage of disease and on dialysis. Anyone with kidney disease, diabetes affecting the kidneys, gout, or a history of an eating disorder should speak to their doctor or a registered dietitian before changing how much protein they eat. The same applies to anyone taking medication for a long term condition.
Why do high protein plans promise more than the trials found?
Because a promise sells and a modest pooled effect does not. A typical plan takes three accurate findings, more filling, slightly more costly to digest, protective of muscle, and turns them into a countdown with a number of pounds attached. None of the trials above support a countdown. They support something plainer: protein can make a calorie deficit easier to live with, and a diet that is easier to live with is one people are more likely to keep.
Protein powders and bars sit in the same pattern. Most of these trials changed ordinary food, and none of the findings here are evidence that a powder or bar does anything the same protein in food would not. A shake is a convenient way to eat protein, not a mechanism of its own, and this site does not recommend any protein product, including the site’s own.
So the honest summary is that it depends, and here is what it depends on: whether the higher intake fits the way you already eat, whether it keeps hunger lower in practice, whether you keep doing it after the novelty wears off, and whether your kidneys and your doctor are on board.
Frequently asked questions
Is a high protein diet the same as a low carb or keto diet?
No. A high protein diet raises the share of energy from protein, and the trials above often kept carbohydrate moderate. Keto is defined by very low carbohydrate and high fat, with protein kept moderate.
Does eating protein at night help with weight loss?
No trial cited here tested timing as the main question. The Leidy review discussed spreading protein across meals at about 25 to 30 grams each as a way to improve fullness, not a particular hour of the day.
Does plant protein work as well as animal protein for weight loss?
The pooled trials above were not designed to separate sources. For people with kidney disease, current kidney guidance favours more plant based protein, which is a reason to discuss sources with a doctor or dietitian.
Will eating more protein make me gain muscle without exercise?
Mostly it helps keep existing muscle while eating less. The large lean mass gains in trials such as Longland came with hard resistance training six days a week.
Can too much protein cause weight gain?
Protein still carries about 4 calories a gram. Adding it on top of everything else eaten adds energy; the trials that found benefits mostly swapped it in for other foods or kept total calories fixed.
Is a high protein diet safe during pregnancy?
Protein needs change during pregnancy, and none of the weight loss trials here studied pregnant women. That question belongs with a midwife, doctor or registered dietitian.
Finished the page? The same five questions from the top, to see what stuck.
This article is general information, not medical advice, and is not a substitute for care from a qualified healthcare professional. Speak to your doctor about your own situation.
Leave a Reply